

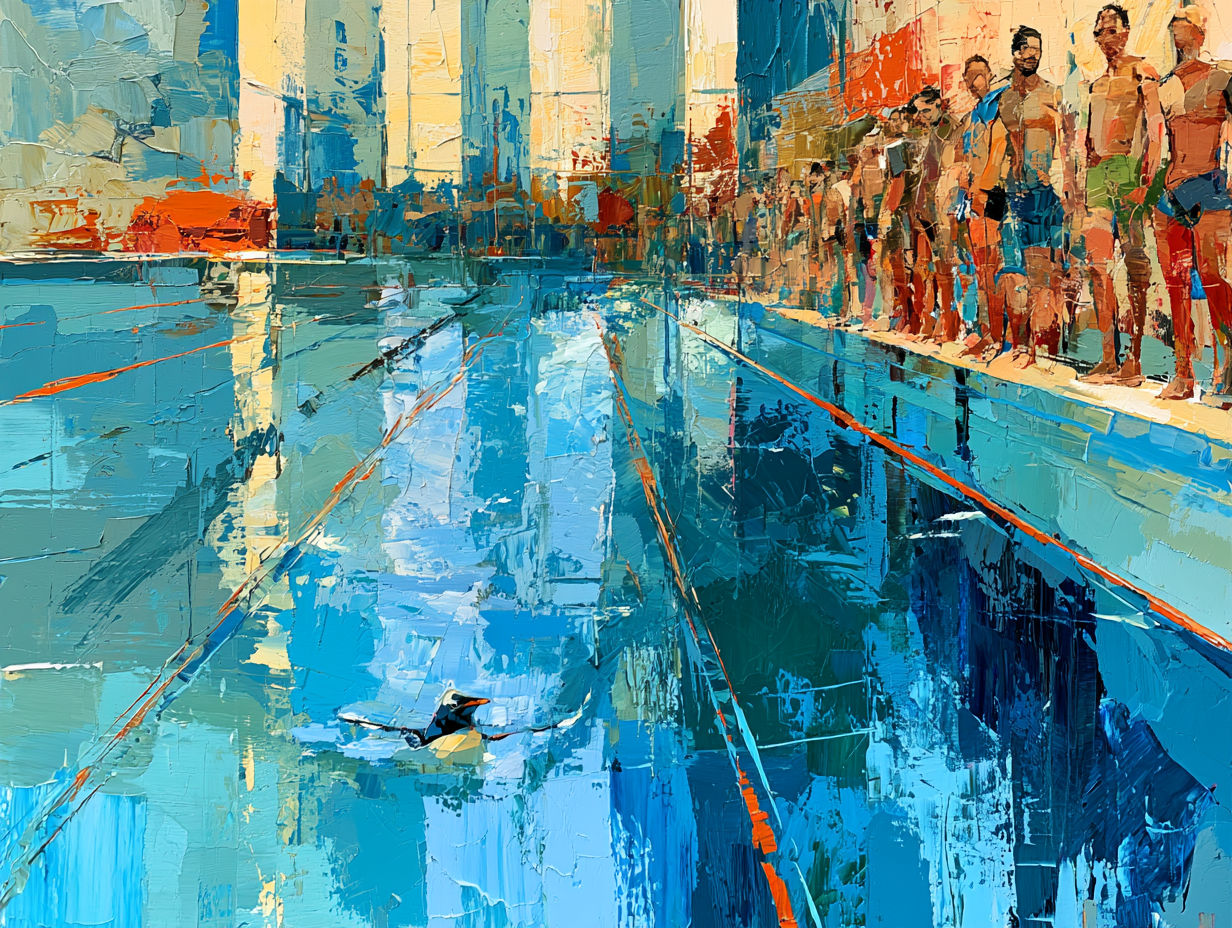
Mental health is usually handed to us as a yes or a no: we have ADHD or we do not, we are depressed or we are not. I find it more accurate to treat every one of these conditions as a spectrum that all of us sit somewhere on, and to notice that each spectrum has an opposite end that rarely gets a name.
The question that follows is one of degree and context: how much, and where does it cost us. A diagnosis marks the far end of one side, the point where a trait has become debilitating at school, at work, or at home. The other far end is often as limiting, and it tends to go unnamed because its costs show up in areas where nobody is evaluating for a diagnosis. Below are the pairs I use most, starting with ADHD, the spectrum where I know my own position best.
There is no variable that does not exist on a continuum.
Why a Diagnosis Reads as Yes or No
A diagnostic manual has to draw a line. Insurance pays or it does not, a school grants the accommodation or it does not, and so the criteria describe the point at which a trait has become a problem that someone has to act on. That line has its uses. It also teaches us to ask whether we have the thing, when the more accurate questions are about degree. What is the degree to which I am depressed? The degree to which I am anxious? The degree to which my attention branches? And in which contexts?
The line hides a second thing, which is the counterweight. Most of the conditions we talk about have an opposite end, and because no criteria were written for that end, we rarely look at it. The same structure runs through every variable of emotional and social intelligence, where each capacity can run too low or too high. We can be too unboundaried or too boundaried. We can be rigidly disengaged from another person or enmeshed with them. We can be so empathetic that we have no filter and immediately embody the emotional energy of everybody in the room, or we can be completely unaware of that energy.
The premise that everything runs by degree sits under all of my own frameworks, from the Fractal Field of Mental Health, my alternative to reading mental health as clusters of symptoms, to The Architecture of Human Systems, my integrative model of psychotherapy.

ADHD and the Linear Mind
The place I diverge most from the usual conversation is the idea that a person either has ADHD or does not. ADHD is a continuum like everything else, and it has a counterweight that rarely gets looked at. I call the counterweight the type A personality, the ultra-linear mind, or, to borrow a Freudian term, the anal retentive.
The ADHD end has a fractal orientation. A fractal is a pattern that keeps branching, each branch splitting into more branches, and a mind at this end does the same with a thought. The other day someone said “swimming pool” and my mind went to penguins. Penguins swim, and a penguin at the zoo lives in what amounts to a swimming pool. From there I was wondering what that life is like for the penguin, then how the zoo keeps the water clean, then whether it is chlorine or bromine, and then what the chlorine does to the penguin. All anyone had said was pool.
The mind at the opposite end is literal and direct. It hears “pool” and sees a pool.
A Fractal Mind That Does Not Qualify for a Diagnosis
I do not have a diagnosis of ADHD, and I would not qualify for one. My mind sits toward the fractal end of the spectrum, and I am also able to do the behavior of linearity quite well. I got good grades in school, so the fractal disposition never became a problem that anyone had to act on.
A diagnosis asks whether the behavior is failing somewhere. The disposition is present either way, and it shapes how I think, what I am good at, and what takes me effort. We can be curious about our range and our disposition even when neither one is problematic.
Why the Linear End Goes Undiagnosed
The linear end goes undiagnosed largely because it does not tend to cause scholastic or vocational problems. A linear mind stays on a task. Asked to go get the laundry, the fractal mind goes a million different places, and the laundry may not arrive. Seated at a desk inside the linear orientation of a school curriculum, a fractal mind has a hard time, and oof, it is painful.
Diagnosis is most common in the places where a trait interrupts what an institution expects of us, and school and work expect linearity. The fractal end has trouble in those settings and gets diagnosed. The linear end fits what those settings ask for, so it never comes to anyone’s attention as a condition.
What the Linear End Costs
The linear end has costs of its own. It interrupts certain creative pursuits and it interrupts imagination. It also interrupts the playful side of communication, which much of the time is a game of improv: one person offers something absurd, and the other accepts it and adds to it.
Suppose I come back from Spain and report that a huge whale jumped, hit the moonbeams, turned into a flying stork, and started coming right at us. The very linear mind answers:
Moonbeams don’t change mammals into other mammals.
The linear disposition has relational implications. They show up in play, in humor, and in imagination, and none of those is an area where anyone is being evaluated for a diagnosis.
A Test Question That Rewarded the Linear Mind
Many tests reward linearity as well. The final exam for my master’s degree asked which marriage and family therapy technique is thought of as most effective for Asians.
I could not get past the question. Which Asians? A Russian? A Korean? A person from India, Bhutan, Kazakhstan? Eventually it dawned on me that the test probably meant a Japanese person, and even that reading was a stereotype. I was lost in the weeds of how a Russian and a person from Vietnam had ended up under one term, as if a continent carries a single cultural identity.
The ethics of that test question are their own subject. The linear mind would have handled the question differently. It would have remembered that for more collectivist and traditionalist societies, a brief and linear approach like solution-focused therapy was probably the answer the test was looking for, marked that answer, and moved on to the next question.

Depression and Mania
Depression and mania are two poles, and there is a range between them. Most of us lean a little toward one pole or the other as a disposition, well short of anything disruptive.
Some people have a more dysthymic disposition, meaning a long-running lean toward the depressive side. They have a harder time finding the motivation to engage in the activities that facilitate positive emotion. Other people run a little manic, though not at the fully disruptive level. They are always psyched and always have a lot of energy. Sometimes that energy is a bit much for the people around them, and a bit much for themselves, because, somewhat paradoxically, people who run this way are very predisposed to boredom.
Context Decides Whether a Lean Helps
The range between depression and mania is a good place to see the importance of context. There are times when being more depressive, more apathetic, is beneficial. I run toward the depressive side in the winter. For me it is a healthy amount of apathy that accommodates the fact that there is nothing to do, like a bear. There are also times when being more manic lets us persevere through extended stretches of energy and task, because there is more daylight. In spring, like most of the animals, I get a little crazy and do excessive amounts of yard work, including picking up rocks that are too heavy for me.
Where Bipolar Disorder Fits
Bipolar disorder, which used to be called manic depression, is a separate matter from the range. It is a diagnosis that includes problems at both poles, and it is one of the few diagnoses that names both. It is a cyclical observation: the person oscillates between two extremes, and each extreme is disruptive. The range sits inside those two extremes, where people lean a little one way or the other depending on their disposition and their context.

Anxiety and Carelessness
Anxiety has to do with our relationship to fear. At the anxious end we take the environment into account to the point where it causes us unnecessary discomfort and dysregulation. That end is in the diagnostic manual. The opposite end usually is not: so little awareness of the environment that we engage it with carelessness and without discernment for danger, including danger of the most practical kinds.
The careless end
Oh, this looks fun. Let’s go down this alley.
We can drive from here to there. No need to think about whether there is a gas station in between.
I’ve never tried to sail across the Atlantic before, but I saw a movie.
The anxious person, at the other extreme, is afraid of a shark in a lake. The shark in the lake is a ridiculous example, and so is sailing the Atlantic because we saw a movie. Each is that far out on its own end. Both ends misread the same thing, which is how much danger the environment holds. The anxious end reads in danger that is absent, and the careless end fails to read danger that is present.

Social Anxiety Has a Counterweight Too
The same spectrum extends into social anxiety. At the anxious end we are overly concerned that everybody is thinking about us, and we are preoccupied with their judgments. At the opposite end we are doing something clearly socially inappropriate, the people around us are showing disturbed nonverbal reactions that are plain to see, and we do not notice them. We all fall somewhere on that spectrum.

Impulsivity and Perfectionism
Another pair runs along intentionality, with impulsivity at one end and perfectionism at the other. The manual sorts this pair unevenly. Impulsivity might be named as something like conduct disorder. A student sees something somewhat phallic-looking in class, screams something inappropriate, and gets in trouble with the teacher. At the impulsive end we say whatever joke comes to mind, released without any forethought about how it will work with the given audience. We see a really cool jump on a bike or on skis and go off it with no information about whether the landing is safe.
At the far other end is perfectionism, where everything is checked. Conversation loses its fluidity, because every sentence passes through a filter of what its outcome could be on the person in front of us. The homework assignment never gets turned in, because it still needs editing for grammar, for voicing, for what exactly we mean. The drive to avoid being wrong or misunderstood interrupts our ability to complete something.
A school or a workplace is likely to notice work that never gets turned in. The cost of perfectionism that often goes unseen is burnout. People at the perfectionist end have no way of accepting “enough,” so they continually push themselves past what is best for their wellbeing. Their perfectionism makes them poor at rest, at recovery, and at balance.
Both of these ends usually envy the other.
The impulsive person wishes for the filter, and the perfectionist wishes for the freedom of not running everything through one.

Guilt and Blame
Anger works as an orientation, internal or external. We can turn it at the self, as shame and guilt, or turn it outward, as blame, and we can be predisposed in either direction.
Take a small piece of feedback. Somebody tells us that we had no way of knowing it, but we put too much mayonnaise on their sandwich. The balanced response sits in the middle: okay, and we fix the sandwich.
At the internal end the same feedback produces guilt and self-shaming.
The internal end
Why did I do that?
How could I?
I’m worried I disappointed this person.
From there the guilt can spiral into deep-seated fears of rejection, for which the person takes full responsibility.
At the external end the anger goes back at the person who spoke. The reply is “well, you didn’t tell me,” even though that person has already said we had no way of knowing and was only giving feedback on the sandwich. The external end moves immediately to blaming, defensiveness, and yelling. Some of us are too quick to take responsibility, and some of us are too quick to blame.

Dependence and Self-Reliance
Dependence is the degree to which we ask for other people’s validation, and the degree to which we ask for assistance before trying ourselves. Its counterweight is the trust we allow ourselves in our own aptitude and skill: asking ourselves to attempt a project we can likely complete before we defer to the assistance of another. A healthy middle does both. It tries first, and it asks when asking is needed.
The far end of self-reliance is never asking for help. It is the stereotype of the man who drives two hours the wrong way in the desert because he did not want to stop and ask for directions. It is the person who is bleeding and will not accept the Band-Aid. At that end help reads as a sign of weakness, when asking for it can hold strength and humility at once.

The Spectrums We Leave Alone
Some dimensions coexist without a diagnostic label on either side. The introvert and the extrovert are the plain example. We allow those to be. That allowance shows what is available for the rest: a way of describing where a person sits, at what degree, in which contexts, and at what cost, without first deciding whether they qualify.
The list of pairs could go on indefinitely, because it is a list of dialectics, and dialectics run through everything (more on how I apply dialectics to civic problems at SolveSomething.com).
Every Position Is Contextual
Where we sit on any of these spectrums is always contextual. Position varies from person to person, and within one person it varies with state. If we are very tired, our position on the anxiety spectrum will move. Relationship moves it as well, which is where attachment theory fits in. In the company of a person we trust we feel less fear, so we have less anxiety and we are more comfortable with risk.
Each of us holds a position on every one of these spectrums at once, and each position moves with the context, the state we are in, and the people we are with. A diagnosis names one of those positions at its far end.


